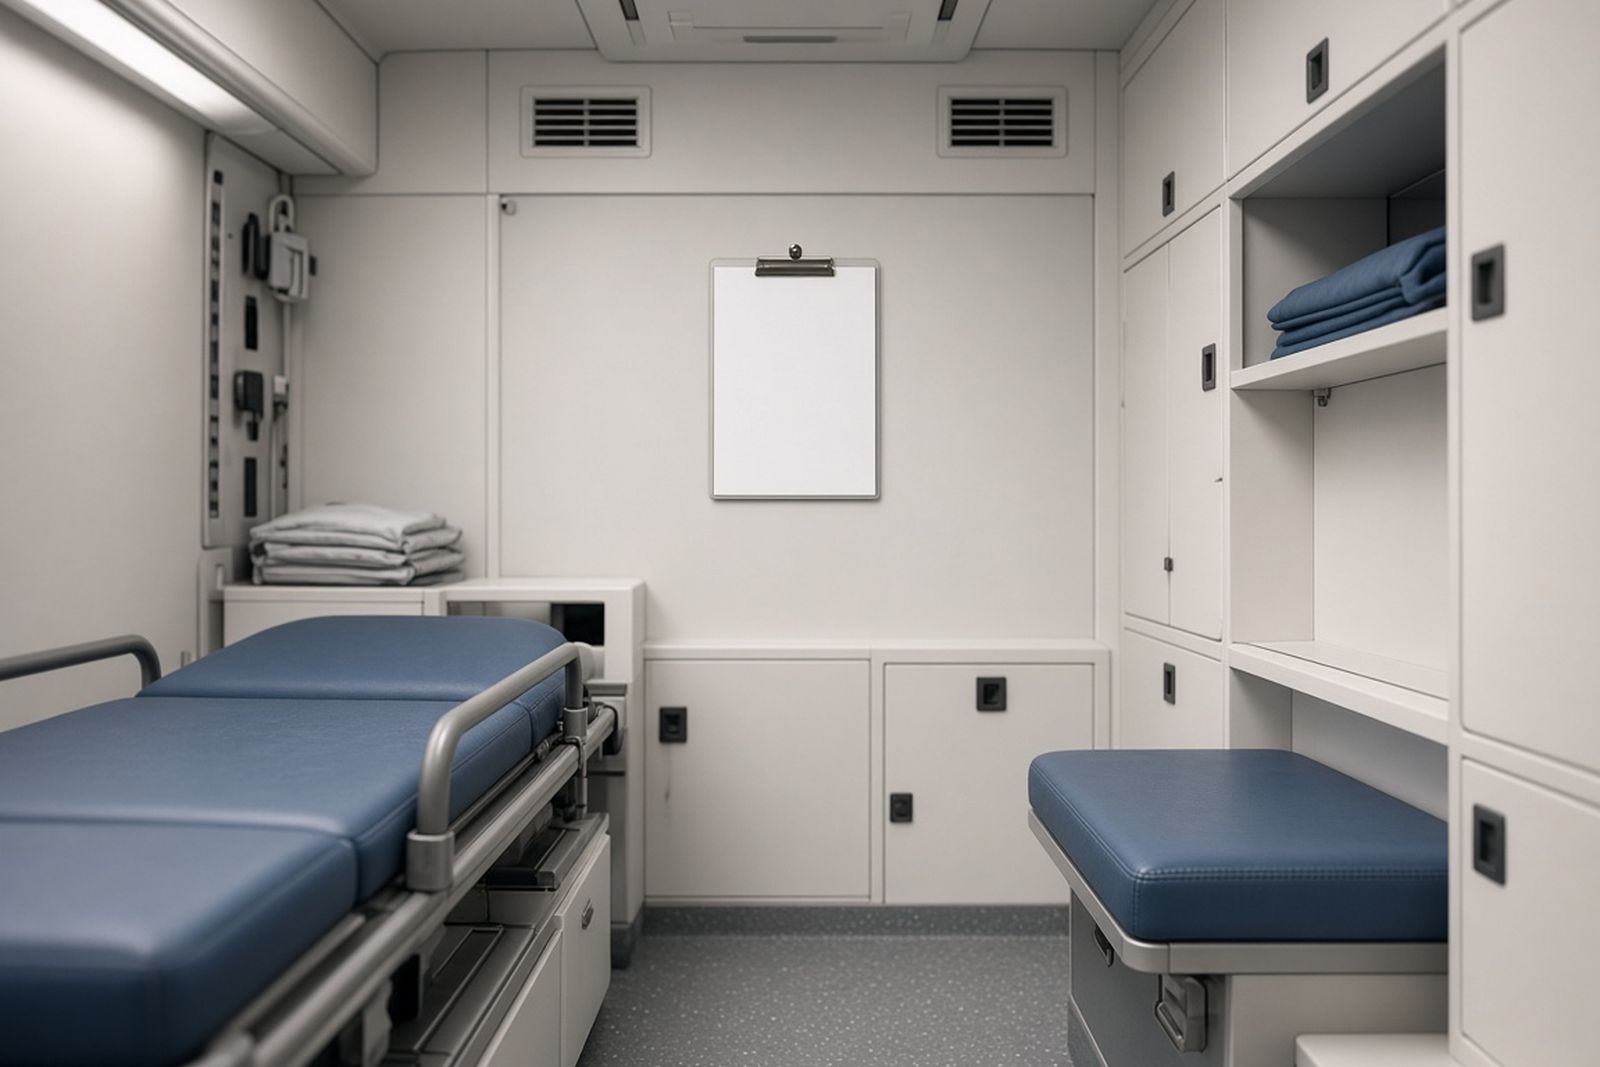
Short answer
Cleaning means physically removing blood, vomit, dirt, and residue from the surfaces of the compartment and cab. Disinfection means applying a registered product that kills the germs left behind, when it stays wet for the time on its label. Your units need both, in that order. Both must use products that are safe for your devices and seat coverings. Soft items that soaked up fluid are usually laundered or replaced.
Two steps, not one
On a busy shift, it is natural to think of decontamination, or decon, as one quick task. Grab a wipe, go over the stretcher, and get back in service. That habit blurs two separate steps. Cleaning removes material from a surface. Disinfection kills the germs left on it. A wipe that does one well may not do the other.
The difference matters because a patient compartment collects mess you can see and mess you cannot. Blood in a floor track, dried vomit on a cabinet edge, or skin oils on a grab rail can all shield germs from a disinfectant. If that residue stays, the disinfectant is working on the surface of the dirt, not the surface of your vehicle.
Knowing the two steps helps you, your crews, and your vendors agree on what a finished decon really looks like.
The same logic applies outside EMS. Think of a patrol car's rear seat after a bleeding arrest, or a fire engine's jump seat after a rescue. The soil has to come off before a disinfectant can do its work. Hard plastic prisoner seats are easier to clean than cloth seats. But seams, seat belt latches, and the partition still collect residue that one spray will not lift.
Cleaning in a patient compartment
Cleaning in a vehicle starts with removing the heavy mess: blood, body fluids, vomit, and debris. Your crews use absorbent materials and throwaway towels. They work from the least soiled areas toward the most soiled. That way they do not drag material across clean surfaces.
Next comes cleaning with detergent and scrubbing. That means wiping or scrubbing surfaces with a cleaning solution, or with a cleaner-disinfectant used as a cleaner. Seams, textured plastics, buckles, latches, and floor tracks collect residue and need extra care. Changing wipes often keeps soil from being spread around.
Some surfaces need more attention. Stretcher mounts, the edges of floor mats, the gap around cabinet doors, and the underside of the bench seat often hold dried material that a quick wipe misses. Taking the stretcher out during a full deep clean lets your crews reach these areas.
Rinsing is sometimes skipped because vehicles have no running water. But some product labels call for it, most of all when a detergent leaves a residue that could get in the way of the disinfectant. A station with a wash bay or decon room makes this easier. Where rinsing is not practical, a clean damp cloth can remove the detergent residue before the disinfectant goes on.
What does disinfection add once the unit is clean?
Disinfection applies a registered product whose label claims it works against the germs you are worried about. The label gives the mixing ratio, the surfaces, and how long the product must stay wet. That wet time is called contact time. Surfaces must look wet for that full time for the product to kill what its label says.
When cleaning and disinfection are done properly, the results can be striking. In a 2025 Saudi hospital study published in Pathogens, 46.08% of 204 ambulance swab samples grew bacteria, but no growth was detected after standard cleaning and disinfection. That result depended on both steps being done, not on disinfection alone.
Meeting the contact time is harder in a vehicle than in a building. Compartments heat up. Air moves through the vents. Liquid runs off upright surfaces. Your crews will often have to apply product again. It helps to choose products with contact times that fit how they work. And they must resist the urge to wipe dry before the time is up.
The surfaces missed most often
In your units, the stretcher, floor, and bench seat get most of the attention. Many other surfaces are touched just as often but cleaned less steadily.
Research has pointed to some surprising places. A 2025 study of five South Korean ambulances in the International Journal of Emergency Medicine found all six tested high-touch surfaces contaminated before daily disinfection, with vents carrying the highest bacterial counts. Vents are rarely on a crew's mental checklist. Yet hands touch them to adjust the airflow, and particles settle on them.
Oxygen equipment deserves a mention of its own. Cylinders, regulators, and flowmeters travel between vehicles, storage rooms, and patients. They are handled all the time. Because they move around, they are easy to leave off one vehicle's decon checklist. Treat them as their own item. Clean and disinfect them whenever they are swapped, and you close that gap.
Other surfaces that are often missed include the items below.
- Air vents and heating and cooling controls
- Overhead grab rails and ceiling-mounted IV hooks
- Cabinet latches and the inner edges of drawers
- Monitor controls, patient cables, and reusable cuffs
- Suction canister holders and oxygen regulators
- Radio handsets, dash computers, and cab controls
- Seat belt buckles and stretcher straps
Safe products and soft items
Cleaning and disinfecting products react with the materials they touch. Your monitors, ventilators, and other devices often come with guidance from the maker on approved products. Vinyl seats, clear plastic panels, and rubber seals can crack, cloud, or turn sticky after repeated contact with the wrong chemicals.
Damaged surfaces are harder to clean the next time. Cracks and pits trap soil and give germs places to hide. Choosing products that suit your surfaces, for both cleaning and disinfection, protects your equipment. It also makes future decon work better.
Some agencies keep this simple. They settle on a small set of products that the makers of their main devices approve. A chart of products and contact times, posted in the station decon area, helps your crews use the right product on the right surface.
Cot mattresses, straps, seat belts, blankets, and cloth restraints soak up fluids. Cleaning and disinfecting the surface cannot reliably reach fluid that has soaked into fabric or foam.
For that reason, many agencies launder or replace soft items after a serious exposure and do not try to disinfect them in the vehicle. A mattress with a sound cover that resists fluid can often be cleaned and disinfected. A mattress with a torn or cracked cover usually has to come out of service.
Keeping spare soft items at each station eases the pressure to reuse items that should be replaced. It also shortens your turnaround, because the unit does not have to wait for laundry.
Personal equipment is much the same. Stethoscopes, penlights, trauma shears, and radio holsters go from call to call on your crew's bodies. They can be cleaned and disinfected, but only if someone remembers to do it. Add them to the end-of-call routine. Then they do not carry germs into a freshly cleaned vehicle.
Between-call wipe vs full decon: two calls compared
Two back-to-back calls, invented for illustration, show the difference. A crew carries a patient with a nosebleed on one call. On the next, the patient cannot stop vomiting.
After the first call, the crew does a clean between calls. They remove a few blood-stained gauze pads. They wipe the stretcher mattress and rails and clean the monitor cable and blood pressure cuff. They apply a cleaner-disinfectant to the touched surfaces. Then they wait the full label contact time before going back in service.
After the second call, vomit has reached the floor, the bench seat, and the lower cabinet doors. The mattress cover has a small tear. The supervisor pulls the unit for a full deep clean. The crew or vendor takes out the stretcher and soft items. They clean the floor tracks and bench seat with detergent and scrubbing, and rinse where needed. Then they apply a disinfectant that is safe for the seat coverings and works against common stomach bugs. The torn mattress is replaced. Vents, grab rails, and cab controls are on the checklist too.
Both responses included cleaning and disinfection. The difference was depth. The second call meant removing more material and reaching more surfaces before the disinfection could be trusted.
Checking both steps, and writing them into your policy
Checking starts with a clear process. Use a written checklist that separates the cleaning steps from the disinfection steps. It should list the surfaces and record the products and contact times. That makes it easier for you to confirm nothing was skipped.
Some agencies put glow-in-the-dark marks on surfaces before decon to see whether they were wiped. Some use a quick swab test that shows leftover organic residue (it does not detect germs). These tools do not test for any one germ. But they can reveal missed surfaces and guide your training.
You or your supervisors can also spot-check units coming back into service. Look for residue in floor tracks, sticky films on panels, and damaged soft items. Keep the feedback helpful. The goal is steady practice, not blame.
Your decon policy should define both terms. It says when each is required and how they fit together for cleans between calls and for full deep cleans. It names the approved products, their contact times, and the surfaces they may be used on.
Your policy should also cover soft items, which products are safe for which devices, protective gear for crews, waste handling, and record keeping. Add police and fire vehicles, not just ambulances, and the policy is more complete.
Check with your state EMS office and medical director. Make sure your policy matches what they expect today and supports both cleaning and disinfection on every unit.


